Health and Fitness
Why have 1 juice recipe, when you can have 4, as part of your detox diet.


detox diet
Why have juice juice 1 recipe, when you can have 4, as part of your detox diet.
Juice extract is becoming popular as a great way to detoxify . Many people are interested in getting toxins out of their system so that they can lead healthier lives. When toxins accumulate in the body, they feel sluggish and have a bad immune system as well.

Employing juice, as a cleansing method, can help people achieve better health and more energy. It is very easy to make as fruit is readily available and only requires a juicer.
For a beginner to hire a juice, it is important to start out slow and try it for one day. By hiring a juice, you limit your intake to juice only. Fruit juice is high in sugar, so if you are diabetic or otherwise need to monitor your sugar intake you should be careful to try a quick juice with fruit juice.
Anyone just starting out with an appointment should speak to their doctor first. Also, do not take juice quickly for long periods like more than 3 days, not unless your doctor agrees that it is safe for you to do so.
detox diet
What are some juice recruitment recipes?
The following are sample recipes to help give you an idea of a variety of fruits and vegetables to use together:
Recipe Fasting Juice 1:
Vegetable juice combo
2 Swiss chard leaves
Beetroot
1/2 Sprigs 2 or 3
Carrot watercress 3 Celery
Stale 1
Wash with strained water or sediment, chop and add juicer.
Recipe Fasting Juice 2:
Carrot-Apple Juice
Green apples 2-3
Carrot 1
Fresh basil leaves
Wash with strained water or sediment, cut and add juicer.
Recipe Fasting Juice 3:
Carrot-Vegetable Juice
A handful of dandelion leaves Kale leaf
1
Carrot 4 Fresh
mint, basil or coriander leaves
Wash with strained water or sediment, cut and add juicer.
Recipe Fasting Juice 4:
Peach juice Peaches 2 or 3
Wash with strained water or sediment, cut and add juicer.
MORE@AFRILATEST detox diet
JOIN US ON FACEBOOK detox diet

Health and Fitness
Zimbabwe’s HIV Gains Face A Test Among Young People
Zimbabwe’s HIV gains face a double test: a rejected $367m US health deal and a young generation that never saw the wards full.

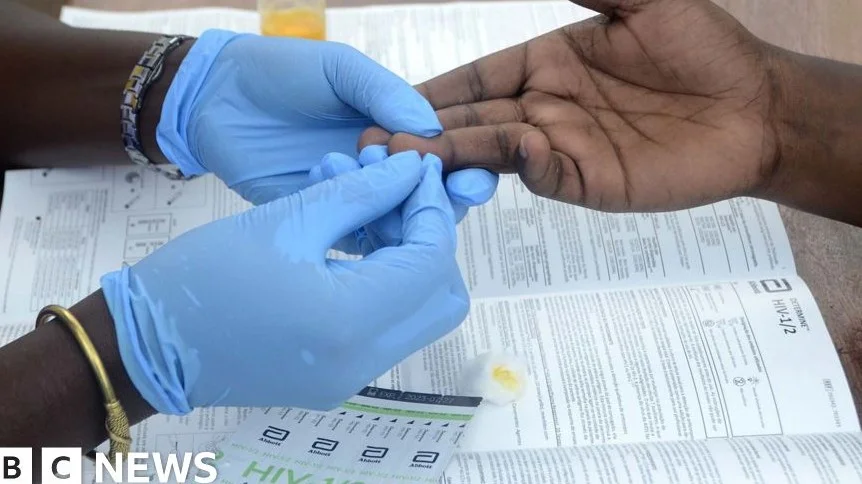
Zimbabwe’s HIV gains are usually told as a single number: new infections down from an estimated 79,000 in 2010 to 15,000 in 2023, according to UNAIDS figures reported by Al Jazeera. Among people aged 15 to 24, the fall ran from roughly 27,000 to 4,400.
Those are estimates, not registries, and they describe a past decade rather than the next one. Two developments now test them at once: the unravelling of the financing model that paid for much of Zimbabwe’s treatment and prevention work, and a cohort of young people who never saw the wards that taught their parents to fear the virus.
What Zimbabwe’s HIV Gains Actually Rest On

The financing side is documented. The US embassy in Harare says Washington provided more than $1.9bn in health funding to Zimbabwe over two decades, and that 1.2 million men, women and children currently receive HIV treatment through US-supported programmes, the BBC reported.
That figure is the crux. Zimbabwe’s HIV gains were never self-financed at scale. They were co-financed, and the co-financier has changed its terms.
Since returning to office, US President Donald Trump has slashed foreign aid and closed USAID, arguing its spending was wasteful. His administration says it is pursuing government-to-government deals instead. The US embassy in Zimbabwe says 16 African countries have signed such pacts, representing more than $18.3bn in new funding.
A Rejected $367m Deal And A Text Nobody Has Published
Zimbabwe is not among the 16. It rejected a five-year package worth $367m (£272m). The decision became public after a government memo dated December was leaked; the BBC reports that President Emmerson Mnangagwa described the arrangement as “lopsided”.

The two governments give different accounts of why. Government spokesman Nick Mangwana said Washington wanted access to biological samples for research and commercial gain without sharing the benefits — vaccines, diagnostics or treatments — that might flow from them. In essence, our nation would provide the raw materials for scientific discovery without any assurance that the end products would be accessible to our people should a future health crisis emerge,” he said.
US ambassador Pamela Tremont framed the loss differently. “We believe this collaboration would have delivered extraordinary benefits for Zimbabwean communities especially the 1.2 million men, women and children currently receiving HIV treatment through US-supported programmes,” she said, adding that Washington would “turn to the difficult and regrettable task of winding down our health assistance in Zimbabwe.”
Separating confirmed fact from claim matters here. Confirmed: the offer was rejected, the sum involved, and the embassy’s winding-down statement. Contested: the precise scope of the data-sharing clause. Neither government has published the agreement text. Zimbabwe’s account of the terms rests on its own officials; Washington’s rests on its embassy.
The dispute is not isolated. The BBC reports that Kenya’s High Court suspended a similar health funding agreement after a consumer rights lobby filed a case citing concerns about the safety of Kenyans’ health data. Mangwana linked the deals to the US withdrawal from the World Health Organization, pointing to the WHO’s Pathogen Access and Benefit Sharing scheme as the model Zimbabwe would prefer.
Why Young People Are The Weak Point
Zimbabwe’s HIV gains are exposed on a second, quieter front. UNAIDS estimated that 210,000 adolescent girls and young women aged 15 to 24 acquired HIV worldwide in 2023. About 160,000 of those infections were in sub-Saharan Africa, and nearly 60 percent of the global total occurred in Eastern and Southern Africa.
In Zimbabwe, Dr Misheck Ruwende, a family physician and stigma-reduction advocate, said in a public address on Twitter in September, followed by Al Jazeera, that the country risked reversing progress “at a time we have the best options to prevent HIV, from rapid testing, PrEP, condoms, PEP to injectables.”

The evidence for a shift in youth attitudes is thinner than the anecdote. Shaun Moyo, a 48-year-old nurse who began at Parirenyatwa Hospital in Harare in the late 1990s and still works locum shifts at two public hospitals, recalls: “In the 90s every weekend was a trek to cemeteries, not weddings.” She cites a Facebook exchange among her son and his friends in which one comment suggested high blood pressure was worse than HIV. That is one observation, not a survey; the sources contain no national youth-attitude data.
The Tools Exist, The Delivery Is The Test
Prevention technology has moved faster than the messaging around it. The PURPOSE 1 Phase 3 trial examined lenacapavir, an injectable given twice a year. In the primary analysis, none of the 2,134 women who received the drug acquired HIV. Dr Linda-Gail Bekker, a co-author of the trial report, argues communication has not kept pace: “Beating the old drum about the horrors of HIV, and shouting to youths about condoms is not necessarily going to cut it.”
Delivery is being rebuilt from the ground up. Angela Gutu, a 23-year-old peer educator, organises pop-up services with the Harare municipality, the health ministry, NGOs and churches at markets, transport hubs, university campuses and sporting events, offering self-testing kits and condoms. “It’s about speaking young people’s lingo, taking away the HIV stigma,” she said.
Dr Innocent Hove, Provincial Medical Officer for Harare Metropolitan Province, told reporters at an August meeting that HIV among young Zimbabweans was an urgent priority, citing decentralised PrEP, PEP, testing and treatment, plus mobile trucks serving informal mining communities.
Funding pressure already reached this layer. UNAIDS reported in March 2025 that disruptions to US-funded HIV programmes in Zimbabwe had affected services for key populations, including PrEP, testing and counselling.
The Bigger Picture
Zimbabwe’s government has not closed the door. Mangwana said the refusal “should not be misconstrued as anti-American sentiment” and welcomed continued dialogue. The Zimbabwe College of Public Health Physicians, while saying it understood the government’s concerns, argued that disputes over data governance “can often be addressed through technical clarification and negotiated safeguards.”
That is the test now running. Zimbabwe’s HIV gains were built on a financing arrangement being renegotiated country by country, and on prevention behaviour every new cohort has to learn for itself. One pillar is being repriced. The other cannot be bought at all.
“My generation was born with the best array of HIV prevention tools,” said Bongani, who plans to volunteer as a peer educator through the health ministry’s programme in January. “It’ll be a tragedy if AIDS deaths make a dramatic comeback due to our reckless behaviours.”
Frequently Asked Questions
Why did Zimbabwe reject the $367m US health deal?
According to government spokesman Nick Mangwana, Washington demanded access to biological samples for research and commercial gain without guaranteeing that any resulting vaccines, diagnostics or treatments would be shared with Zimbabwe. President Emmerson Mnangagwa reportedly called the deal “lopsided” in a December memo that was later leaked. The full agreement text has not been published by either side.
How much has the US spent on health in Zimbabwe?
The US embassy in Harare says Washington has provided more than $1.9bn in health funding to Zimbabwe over the last two decades, and that 1.2 million people currently receive HIV treatment through US-supported programmes.
How much have new HIV infections fallen in Zimbabwe?
UNAIDS estimates annual new infections fell from 79,000 in 2010 to 15,000 in 2023. Among people aged 15 to 24, infections declined from about 27,000 to 4,400 over the same period. These are modelled estimates rather than counted case registries.
 Follow AFRILATEST on Google News
FIRST TIME REACTIONS:
Be the first to leave us a comment – Zimbabwe’s HIV Gains Face A Test Among Young People, down the comment section.
JOIN US ON OUR SOCIAL MEDIA:

About Paul Nwogo
Paul Nwogo is an engineer, published author, and the Head Manager at AfriLatest. He has written numerous books available on Amazon covering a diverse range of topics, including health, personal finance, relationships, work ethics, and scam survival. With his technical background and passion for writing, Paul now oversees the editorial direction of AfriLatest, delivering practical, accurate, and engaging content on trending news, music, and global lifestyle topics.
Health and Fitness
Hair Dye Safety: What Works, What Doesn’t, What’s Unproven
A practical hair dye safety guide: patch tests, bleach timing and scalp care, using celebrity colour changes as a cautionary case study.

The outcome you want is straightforward: a new colour that looks good, holds up, and leaves your scalp where it belongs. The fastest way to lose it is to copy a celebrity’s finished result while skipping the part of the process nobody photographs. That gap is where hair dye safety usually fails.
Jacob Elordi spent a weekend in New York City hiding his. According to Elle, the actor was photographed on two dates with Kendall Jenner, at Paranormal Activity on Broadway on Saturday and outdoors in fall layers on Sunday. He wore a beanie both times and added a hoodie on the second day for extra coverage. Even so, a patch of blond showed at the back of his hat. He has not said why he changed colour, and he has not shown the full look.
That concealment is a useful starting point for a health conversation, because it separates the outcome from the process. Blond is a result. Testing, timing and a professional who knows what your scalp can take is the process. Most hair damage happens when someone chases the first without the second.

Why Hair Dye Safety Matters More Than The Shade
Your scalp is skin. It absorbs, it reacts, and it remembers.
A dye applied to a calm scalp and the same dye applied to skin that is already irritated or freshly relaxed are not the same event. Dermatologists and dye manufacturers have long recommended patch testing before application, and most box kits carry the instruction on the leaflet. Allergic reactions to hair colour are a recognised, documented problem, not a freak accident. This is the strong end of the evidence: contact allergy to dye chemicals exists, it can develop after years of uneventful use, and once it appears it tends to persist.
The weak end is where most online argument lives. Questions about repeated dye exposure and long-term cancer risk have been studied for decades with mixed results. Research is still ongoing. No single study justifies panic, and no single study justifies dismissal either. Anyone who tells you the matter is settled is selling something.
What the celebrity coverage does establish is narrower and more reliable: professionals do not apply colour to an untested scalp, and they do not treat colour as a five-minute decision.

Hair Dye Safety Steps That Actually Hold Up
First, patch test 48 hours ahead. A small amount of dye behind the ear or on the inner forearm, left alone, tells you what your immune system thinks before your whole head finds out. Skip this and you are gambling on a reaction you cannot undo.
Second, be honest about your hair’s history. A relaxer, a recent henna application or a bleach job from six weeks ago changes what the next chemical can safely do. Salons in Lagos, Accra and Nairobi handle this daily, and the good ones ask. If yours does not ask, volunteer it.
Third, treat bleach as the serious step it is. Lifting dark hair to blond means removing pigment, and removing pigment means chemical stress on the shaft. Doing it in one sitting to save time raises the odds of breakage and scalp burns. Two sessions with a gap between them is slower, and safer.
Fourth, know what natural means on a label. Henna and herbal dyes are not automatically gentler. So-called black henna has been repeatedly flagged by dermatologists and regulators because it is often mixed with the same dye chemicals used in conventional colour, and applied to skin rather than hair. A plant on the box is not a safety guarantee.
Fifth, space out chemical services. Colour, relaxer and bleach inside the same fortnight is a schedule for damage. Give the scalp weeks, not days.
The Mistakes That Undo Everything

The biggest one is chasing a specific shade in a single appointment. The second is dyeing over an irritated scalp because an event is coming. The third is assuming a salon visit is protection. A salon reduces risk. It does not remove risk, and no stylist can test your immune system on your behalf.
None of this is exotic. Hair dye safety is mostly bookkeeping: what your scalp has already been through, and when.
It is worth noting that AOL reported Jenner’s platinum bob at the end of October, worn for a Paris, Texas Halloween costume. The same report notes she had gone blonde before, for looks referencing Pamela Anderson and Marilyn Monroe. Even with professional teams, this is a repeated, staged exercise across years, not one dramatic afternoon. AOL also reported that actor Paul Anthony Kelly went bleach blonde for a television role, in his case with highlights styled around the part rather than a full-lift from dark.
Meanwhile, AOL UK reports that Olivia Jade has been photographed in New York with art dealer PC Valmorbida following her reported split from Elordi. Personal lives move quickly. Scalp recovery does not.
Your First Step Today
Before you book anything, arrange a patch test. If you are using a box dye, test with the product you intend to apply, not a different brand. If you are going to a salon, ask to be tested before the appointment, and if they refuse, take your scalp somewhere else. That single step is the difference between hair dye safety being a phrase in an article and something you have actually done.
The realistic result is a colour you wanted, on a scalp that is not itching, weeping or shedding. You will not get certainty about every long-term question, because nobody can give you that today. What you get is control over the risks that are known and manageable, and a habit of not treating a preliminary headline as a diagnosis.
Frequently Asked Questions
Do I really need a patch test before dyeing my hair?
Yes. Patch testing 48 hours ahead is standard guidance from dye manufacturers and dermatologists. It will not predict every reaction, but it is the cheapest way to find out whether your skin tolerates a product before it goes on your whole scalp.
Is hair dye linked to cancer?
The research is mixed and still ongoing. Studies over several decades have not produced a settled answer, and no single study justifies either panic or dismissal. The risks that are well documented and manageable are skin-related: irritation and contact allergy.
Are natural or herbal dyes safer than conventional ones?
Not automatically. Products marketed as black henna, for example, have been repeatedly flagged because they are often mixed with the same dye chemicals found in conventional colour. Read the ingredient list rather than the front of the box.
FIRST TIME REACTIONS:
Be the first to leave us a comment – Hair Dye Safety: What Works, What Doesn’t, What’s Unproven, down the comment section.
JOIN US ON OUR SOCIAL MEDIA:
About Paul Nwogo
Paul Nwogo is an engineer, published author, and the Head Manager at AfriLatest. He has written numerous books available on Amazon covering a diverse range of topics, including health, personal finance, relationships, work ethics, and scam survival. With his technical background and passion for writing, Paul now oversees the editorial direction of AfriLatest, delivering practical, accurate, and engaging content on trending news, music, and global lifestyle topics.
View all articles by Paul NwogoHealth and Fitness
Bauchi Trains Health Workers In Nutrition Commodity Forecasting
Bauchi trained health workers in nutrition commodity forecasting for MMS and iron-folic acid. What the method fixes, and where the evidence thins out.

The outcome you want is unglamorous. A pregnant woman walks into a primary healthcare centre in Ganjuwa and the iron and folic acid tablets are on the shelf. Not ordered, not in transit, not promised for next week. On the shelf, that morning.
Reaching that point is an arithmetic problem before it is a clinical one. Someone has to know how many women will attend next quarter, how many tablets each will need, how much is already in the store, and when the stock already sitting there expires. Bauchi State has just taken a group of health workers through that arithmetic under the name nutrition commodity forecasting.
The two-day exercise, run by Nutrition International with the Bauchi State Primary Health Care Board and the Bauchi State Drugs and Medical Consumables Management Agency, covered multiple micronutrient supplementation (MMS) and iron and folic acid supplementation (IFAS), Leadership reported. Participants came from four local government areas and included maternal and child health officers, nutrition focal persons, essential drugs officers, store officers, procurement staff and logisticians.
What Nutrition Commodity Forecasting Actually Fixes
Both supply failures hurt patients, and they hurt differently. Understocking means a woman leaves the clinic without tablets. Overstocking means money sits on a shelf until it expires, and that same money is unavailable for something else it was meant to buy.
Asabe Emmanuel Lekwot, Nutrition International’s state coordinator, put both in one frame: overstocking and understocking alike can undermine the delivery of nutrition services. Forecasting is the discipline that sits between those two failures. It treats nobody. It decides whether the treatment exists when the patient arrives.
That distinction matters in a country where nutrition commodities compete for the same scarce naira as everything else in a facility’s budget. A forecast that is wrong by a wide margin does not just create an empty shelf or a full store. It makes the next budget request easier to dismiss.
The Steps, In The Order That Works

First, choose the forecasting method that matches the data you actually hold. The Bauchi sessions covered four approaches: consumption-based forecasting, service-based forecasting, morbidity-based forecasting and demographic forecasting. Consumption-based uses records of what was dispensed. Service-based uses expected attendance at the facility. Demographic uses the population the facility serves.
Second, pull the real records. Facilitators built the practical exercises around consumption records, demographic information and health service statistics. This is where most facilities stall, because the numbers exist but are scattered across registers.
Third, convert those records into a requirement figure for a defined period, whether a quarter or a year.
Fourth, compare the figure with stock on hand, and check expiry dates. Pharmacist Ubale Ahmed, the lead facilitator and warehouse manager, described sessions built around identifying excess stock and monitoring expiry, not only calculating what to order.
Fifth, cost the requirement. Lekwot’s framing is that accurate forecasting lets a facility state its commodity and funding needs over a specific period, which is what makes procurement and distribution planning possible.
Sixth, put the number into a budget document. Ahmed noted the timing: ministries, departments and agencies were preparing their 2027 Annual Operational Plans. A forecast that misses that window is an academic exercise.
Seventh, write it up. Participants were introduced to technical report writing and to using forecasting results as evidence for advocacy and resource mobilisation.

Where The Evidence Holds And Where It Thins
The methods themselves are not experimental. Consumption-based and service-based quantification are standard supply-chain practice, and the failure modes named at the training are ordinary ones. Ahud Juji Madaki, officer-in-charge of Dabe Primary Healthcare Centre, described how thin knowledge of quantification leads workers to order beyond actual need, leaving stock to accumulate. That is a mechanism, not a hypothesis.
What the reporting does not establish is whether the training changed anything measurable. There is no baseline stockout rate for the four local government areas, no list of facility counts, no post-training availability check. Bauchi has 20 local government areas; this covered four. A two-day workshop producing better forecasts is a reasonable expectation, but expectation is not evidence. Research on how training translates into supply-chain performance at facility level is still ongoing, and anyone claiming a verified drop in stockouts from this exercise would be going beyond what has been published.
The clinical side deserves the same care. Multiple micronutrient supplementation is not a fringe product, but its guidance is not unconditioned either. The World Health Organization’s antenatal care recommendations frame MMS during pregnancy with qualifications attached, including use in the context of rigorous research. That is a signal worth holding onto: procurement decisions and clinical certainty are two different things, and neither should be borrowed from the other. Vitamin supplements are not a cure for poor maternal diets, and no forecasting system, however accurate, feeds anyone.
Mistakes That Undermine Nutrition Commodity Forecasting
Ordering from instinct instead of registers. The commonest error described by participants is ordering more than the data supports, because the cost of running short feels worse than the cost of a crowded store. It is not.
Ignoring expiry until the audit. Excess stock that expires is not a cushion. It is a loss that has already happened.
Building the forecast after the budget is set. If the number arrives after the annual operational plan is signed, the facility spends another year working around a figure it did not choose.
Treating the technical report as paperwork. The report is the document that carries the facility’s requirement into a conversation about money. Left in a drawer, it changes nothing.
Training one person and stopping there. Haima Ahmad of Kafin Madaki Primary Healthcare Centre singled out the practical sessions as the most valuable part of the training. Skills learned hands-on survive transfers of staff better than those absorbed from a slide.
Umar Alhaji Shehu of Faguji Primary Healthcare Centre in Giade made the point that closes the case for the method: the same skills apply beyond nutrition commodities, to ordering across other essential services. That is the real return. Not a single better tablet order, but a facility that can count.
The first step is available today and costs nothing. Walk to the store, count what is on the shelf, write down the expiry dates of the oldest stock, and put that against the last three months of dispensing records. If the two numbers do not tell a sensible story, the facility has a nutrition commodity forecasting problem, and it is better to find it now than at the end of the quarter when a woman is standing at the counter and there is nothing to give her.
Frequently Asked Questions
What is nutrition commodity forecasting?
It is the process of calculating how much of a nutrition product, such as iron and folic acid tablets or multiple micronutrient supplements, a health facility will need over a set period. It uses records of past consumption, expected service attendance, demographic data or disease patterns, then compares that figure with stock on hand and expiry dates so orders and budgets match real need.
Does this training prove Bauchi has reduced stockouts?
No. The published report describes the training content and participants but gives no baseline stockout data and no post-training measurement. Better forecasting is a reasonable expectation from the skills taught, but a verified change in commodity availability would require facility-level data before and after, which has not been reported.
Are multiple micronutrient supplements a proven treatment for poor maternal nutrition?
They are a supplement, not a treatment for poor diet. The World Health Organization’s antenatal care recommendations include multiple micronutrient supplementation during pregnancy with conditions attached, including use in the context of rigorous research. Accurate forecasting ensures the product is available if a facility decides to provide it; it says nothing on its own about clinical benefit.
Receive alerts for nutrition commodity forecasting and more like it.
FIRST TIME REACTIONS:
Be the first to leave us a comment – Bauchi Trains Health Workers In Nutrition Commodity Forecasting, down the comment section.
JOIN US ON OUR SOCIAL MEDIA:
About Paul Nwogo
Paul Nwogo is an engineer, published author, and the Head Manager at AfriLatest. He has written numerous books available on Amazon covering a diverse range of topics, including health, personal finance, relationships, work ethics, and scam survival. With his technical background and passion for writing, Paul now oversees the editorial direction of AfriLatest, delivering practical, accurate, and engaging content on trending news, music, and global lifestyle topics.
View all articles by Paul Nwogo-

 Car Reviews1 week ago
1955 Chevy Bel Air Restomod: What SEMA Really Proves
-
Startups2 months ago
What a Successful Dangote Refinery IPO Really Says
-
Health and Fitness1 month ago
Curly Hair Hydration: 5 Proven Steps That Actually Work
-
Savings & Investing3 weeks ago
Hidden Medicare Fees Draining Your Retirement Savings
-
Tech & Gadgets1 month ago
Apple Watch and AirPods Fall Deals: Save $120 Today
-
Health and Fitness4 weeks ago
9 Best Hair Thickening Shampoos for Men in 2026
-
University Admissions2 months ago
UNILAG 2026/2027 Admission: Direct Entry & Post-UTME Guide
-
Football2 months ago
South Carolina vs Alabama: Tide Roll to 35-10 Halftime Lead