
Health and Fitness
Nutrition Emergency: 36 Governors Launch N65bn Fund
Nigeria’s 36 governors declare a nutrition emergency, launching a National Nutrition Intervention Fund and N65bn food bank to fight child malnutrition.


The fitness goal here is not personal—it is national. Nigeria’s 36 state governors have declared a nationwide nutrition emergency. Their plan: establish a National Nutrition Intervention Fund to support the Nutrition 774 Initiative across all 774 local government areas. This is the biggest coordinated push against child malnutrition the country has seen.
But what does it mean for you, your family, and your community? And how can you plug into it?
Warm-Up: What Exactly Was Announced

Governor Dauda Lawal of Zamfara read the Nigeria Governors’ Forum (NGF) Addis Ababa Commitment on Nutrition in Ethiopia. The commitment followed a three-day Nigeria-Ethiopia Nutrition Leadership Exchange led by Vice President Kashim Shettima. The Nigerian delegation studied Ethiopia’s Seqota Declaration—a programme that reduced stunting through sustained political leadership.
The governors resolved to declare a nutrition emergency, create the National Nutrition Intervention Fund, and adopt a “One Goal, One Plan and One Budget” approach for nutrition. They also pledged to strengthen domestic financing and extend the National Nutrition Scorecard to local government and ward levels.
This matters because Nigeria has the second-highest number of stunted children in the world. About 32 per cent of children under five have stunted growth. That is roughly 12 million children, according to Minister of Agriculture and Food Security Abubakar Kyari.
Main Routine: The Three Pillars of the Nutrition Emergency
Pillar 1: The National Nutrition Intervention Fund
The fund will incentivise state-level leadership, encourage domestic investment, reward effective implementation, and support measurable improvements. It is not a one-off donation. It is a financing mechanism meant to keep money flowing to where it is needed most—communities and wards.
Pillar 2: The Community Food Bank Programme
Separate from the NGF fund, the First Lady, Oluremi Tinubu, launched the National Community Food Bank Programme. Over N65 billion was raised at the inauguration. The Aliko Dangote Foundation pledged N20 billion over five years. The Federal Government pledged N17 billion through the Social Action Fund. The NGF matched with N17 billion. NNPC Limited pledged N10 billion. The First Lady personally pledged N500 million. The Sir Emeka Offor Foundation pledged N500 million. Anonymous supporters gave $500,000.
The programme targets 500,000 households in its first year. It focuses on children under six, pregnant women, and nursing mothers. Distribution will happen through Primary Health Centres using a voucher system. Beneficiaries will receive locally sourced nutritious food at designated community food banks.
The Bank of Agriculture will manage the fund with strict transparency: multi-signatory approvals, independent audits, and real-time reporting. “No single person can authorize a disbursement,” said Managing Director Ayodeji Sotinrin. “A minimum of three to five authorised trustees must co-sign every approval.”
Pillar 3: Targeted State Interventions
The NPHCDA will begin targeted nutrition interventions in two states with a high burden of stunting. The plan will be costed, with joint financing between federal and state governments. Review meetings are proposed at three, six, and nine months, with progress reported to the Vice President through the National Council on Nutrition.
Cool-Down: What You Can Do Today
You do not have to wait for the fund to reach your ward. Here are practical steps:
First, know your child’s nutritional status. Take them to the nearest Primary Health Centre for growth monitoring. Stunting is measured by height-for-age. It is not always visible.
Second, use local foods. Eggs, beans, groundnut, crayfish, dark green vegetables like ugu and efo tete, and orange-fleshed sweet potatoes are nutrient-dense. A child’s plate should have variety, not just volume.
Third, attend antenatal and postnatal clinics. Nutrition for pregnant and nursing mothers directly affects child outcomes.
Fourth, if you are in a community with a food bank or voucher programme, ask your ward health worker how to enrol. The programme is designed to reach vulnerable households through PHCs.
Fifth, support community-based nutrition. The First Lady said even one naira adds up. If you can volunteer or contribute, you strengthen the system.
Frequency: How Often to Act
Nutrition is daily, not seasonal. Feed children diverse meals every day. Check growth monthly for under-fives. Attend clinic visits as scheduled. For community leaders, hold ward-level nutrition meetings quarterly to review progress.
Tips for Making It Work
Focus on the first 1,000 days—from pregnancy to age two. That window determines much of a child’s future health and brain development.
Use data. The governors committed to state-specific surveys and scorecards. Ask your local government for nutrition data. Hold them accountable.
Avoid rumours. The programme is new. Details on enrolment will come through official PHC channels. Do not pay anyone to register.
How to Know It Is Working
You will know the nutrition emergency is working when your ward health centre has food supplies for vulnerable children. When stunting rates in your local government drop. When mothers receive vouchers without hassle. When the National Nutrition Scorecard shows improvement at ward level.
At home, you will know it is working when your child gains weight steadily, eats a variety of local foods, and stays active. When clinic visits show normal growth.
This is a long race, not a sprint. The commitments are signed. The money is pledged. Now comes implementation. Your role is to use the services, demand accountability, and feed your family well with what is available.
For more details, read the Premium Times report, the Arise News coverage, and The Nation’s report on the food bank.
If your child shows signs of severe malnutrition—swollen feet, peeling skin, extreme weakness—go to a hospital immediately. Do not wait for a programme.
Frequently Asked Questions
What is the Nutrition 774 Initiative?
The Nutrition 774 Initiative is a Nigerian programme aimed at tackling malnutrition across all 774 local government areas. It is supported by the National Nutrition Intervention Fund, which the 36 state governors agreed to establish during the Nigeria-Ethiopia Nutrition Leadership Exchange in Addis Ababa.
How will the National Nutrition Intervention Fund help ordinary Nigerians?
The fund is designed to incentivise state-level leadership, increase domestic investment, reward effective implementation, and support measurable nutrition improvements. It will finance nutrition activities at local government and ward levels, making it easier for communities to access resources.
What is the Community Food Bank Programme?
The Community Food Bank Programme is a federal government initiative that targets 500,000 households in its first year, focusing on children under six, pregnant women, and nursing mothers. It uses Primary Health Centres and a voucher system to distribute locally sourced nutritious food. Over N65 billion was raised at its launch.
Related Articles
- Anthropic Can’t Control Its AI Agents: What It Means
- Nutrition Leadership: What Nigeria Can Learn From Ethiopia
- Kiz Nation Expands: Naira Marley, Mohbad Ties
- SynthID Detector: How to Spot AI Fakes in 3 Steps
- Israel Trains Nigerian Health Professionals on Emergency Maternal Care
 Follow AFRILATEST on Google News
FIRST TIME REACTIONS:
Be the first to leave us a comment – Nutrition Emergency: 36 Governors Launch N65bn Fund, down the comment section.
JOIN US ON OUR SOCIAL MEDIA:








Health and Fitness
Princess of Wales Cancer Documentary: How to Watch Heal
The Princess of Wales cancer documentary Heal airs on NBC. A practical guide to what the film shows, what it cannot prove, and how to use it.

Cancer survivors in Lagos, Nairobi and London ask the same question after every celebrity health story: is there anything here I can actually use? The Princess of Wales cancer documentary Heal arrives on NBC on Nov. 30 with a clear answer and an equally clear limit. The film follows Catherine through Britain’s National Three Peaks Challenge and through her own reflections on life after treatment. It is a first-person account of recovery. It is not a clinical trial, a treatment protocol, or a cure. Telling those three apart is the skill this guide teaches.
The reach matters. The BBC airs the film in the UK on Nov. 29 at 6:15 p.m. GMT. NBC carries it in the United States on Nov. 30 at 8 p.m. ET/PT, with a Bravo broadcast at 11:30 p.m. and streaming on Peacock from Dec. 1. Channel 9 shows it in Australia on Dec. 1 and CTV in Canada on Dec. 7. For most viewers in Nigeria, Ghana or Kenya, the film will not arrive as a 90-minute broadcast. It will arrive as a 30-second clip on WhatsApp, stripped of everything except the emotion.
What The Princess Of Wales Cancer Documentary Actually Shows

The trailer dropped on Saturday, Nov. 21, according to People. Detail Films produced the special and Benji Jackson directed it, with a score by Erland Cooper. Cameras followed Catherine in June as she climbed the highest mountains in Scotland, England and Wales within 24 hours in support of the Royal Marsden Cancer Charity. Her brother James Middleton appears, as do Prince William and their three children.
The medical timeline is public. She announced in March 2024 that she was undergoing chemotherapy following major abdominal surgery, completed chemotherapy that September, and said in January 2025 that she was in remission. She became joint patron of the Royal Marsden in January 2025. NBC News notes one detail worth holding onto: she has not disclosed what type of cancer she was treated for.
In the trailer she says cancer “changes your body, it changes you physically. But there’s a much, much deeper part to what a cancer diagnosis shifts in you.” She describes healing as a journey, and finding “a sense of hope and joy alongside uncertainty.”
Separate A Recovery Story From A Treatment Protocol
Here is the first step in reading any celebrity health narrative correctly: decide what kind of evidence you are looking at. A single patient’s account can establish what an illness felt like. It cannot establish which treatment worked, at what dose, or how often it works across a population. Those questions need cohorts, control groups and follow-up data. None of that is in this film, and the film does not claim it is.

The strongest, most transferable content is emotional. Recovery does not end when chemotherapy ends, and the trailer makes that plain. The conversation with James Middleton carries the point further. He asks whether she rang the bell at the Royal Marsden, the tradition that marks the end of treatment. She says she did not. He suggests the climb might be her bell.
The second step is refusing to copy the physical load. Climbing three national peaks inside 24 hours is an endurance feat, performed in remission, with a support crew and a filming schedule. It is not a rehabilitation target for anyone else. Movement during and after cancer treatment sits inside mainstream care, but the dose is set by your oncologist and your blood counts, not by a documentary.
The third step is keeping “holistic care” in its proper place. NBC said the film aims to help others through diagnosis and recovery and to improve access to holistic care that supports wellbeing and quality of life. That is support alongside treatment. No mainstream oncology body treats mountain air, nature or emotional processing as a replacement for surgery, chemotherapy or radiotherapy.
Mistakes To Avoid When A Cancer Story Trends
Assuming the film reveals the regimen. It does not. With the cancer type undisclosed, anyone selling a “Kate protocol” online is fabricating.
Reading remission as cure. Remission means no detectable evidence of disease. Follow-up scans continue, and the film’s own framing is life after diagnosis, not life after medicine.
Sharing clips without context. This is the likeliest failure mode in Africa. A forwarded video that shows a smiling woman on a mountain will travel faster than a paragraph explaining that she was in remission and medically cleared.

Assuming the money reaches African clinics. All proceeds from distribution go to the Royal Marsden Cancer Charity, a British hospital charity. Nothing in the announced distribution plan names an African institution. That distinction matters in health systems where patients meet costs at the point of care rather than through a state-funded service.
Turn The Film Into Questions For Your Own Doctor
Write these down before your next appointment. What type of cancer was I treated for, and what does my last scan actually show? What does remission mean for my specific disease? What physical activity is safe for me now, and what should I stop? What psychological support exists here, and what does it cost? Is there a comprehensive cancer centre within reach, and what does a referral require?
USA TODAY reports that Catherine described the challenge as a chance to explore life beyond diagnosis and to give something back. The Hollywood Reporter confirms that all money from distribution goes to the charity. Both facts are straightforward. Neither is clinical guidance.
Your First Step Today
Watch the Princess of Wales cancer documentary if you can, and take its permission seriously: talk about the fear, the changed body, the uncertainty that survives the final infusion. Take nothing else from it literally. Then do the one thing a film cannot do for you. Book an appointment, carry three written questions, and bring someone who will write down the answers.
Frequently Asked Questions
When and where can I watch Heal, the Princess of Wales cancer documentary?
It airs on the BBC in the UK on Nov. 29 at 6:15 p.m. GMT, on NBC in the US on Nov. 30 at 8 p.m. ET/PT, on Bravo at 11:30 p.m., and streams on Peacock from Dec. 1. Channel 9 shows it in Australia on Dec. 1 and CTV in Canada on Dec. 7. No Nigerian broadcaster has been announced in the distribution plan reported so far.
Does the documentary reveal what treatment the Princess of Wales received?
No. She announced in March 2024 that she was having chemotherapy after abdominal surgery, completed it in September 2024 and reported remission in January 2025. She has not disclosed the type of cancer she was treated for, and no regimen is named in the film.
Can I copy the Three Peaks Challenge as part of my own cancer recovery?
It is not a rehabilitation template. Climbing the highest peaks in Scotland, England and Wales within 24 hours is an endurance feat performed in remission with a support team. Physical activity is part of mainstream cancer care, but the safe dose depends on your diagnosis, treatment stage and blood counts, and should be set by your oncology team.
FIRST TIME REACTIONS:
Be the first to leave us a comment – Princess of Wales Cancer Documentary: How to Watch Heal, down the comment section.
JOIN US ON OUR SOCIAL MEDIA:

About Paul Nwogo
Paul Nwogo is an engineer, published author, and the Head Manager at AfriLatest. He has written numerous books available on Amazon covering a diverse range of topics, including health, personal finance, relationships, work ethics, and scam survival. With his technical background and passion for writing, Paul now oversees the editorial direction of AfriLatest, delivering practical, accurate, and engaging content on trending news, music, and global lifestyle topics.
View all articles by Paul NwogoHealth and Fitness
Nigeria’s Health Funding Crisis: A Remedy Nobody Has Tested
Nigeria’s health funding crisis has a four-year deadline. What the evidence on domestic financing actually shows, and what remains unproven.

Nigeria’s health funding crisis now has a name, a number and a deadline. The name is donor dependency. The number is a projected $280 million reduction in United States support. The deadline, according to the federal government’s own assessment, falls within four to five years.
That framing matters. The remedy being promoted across African health ministries, domestic financing, rests on a simple argument: countries should fund their own nurses, vaccines and laboratories instead of waiting on Washington. Parts of that argument sit on solid evidence. Parts of it are being sold with more confidence than the data carries.
What The Health Funding Crisis Looks Like In Hard Numbers
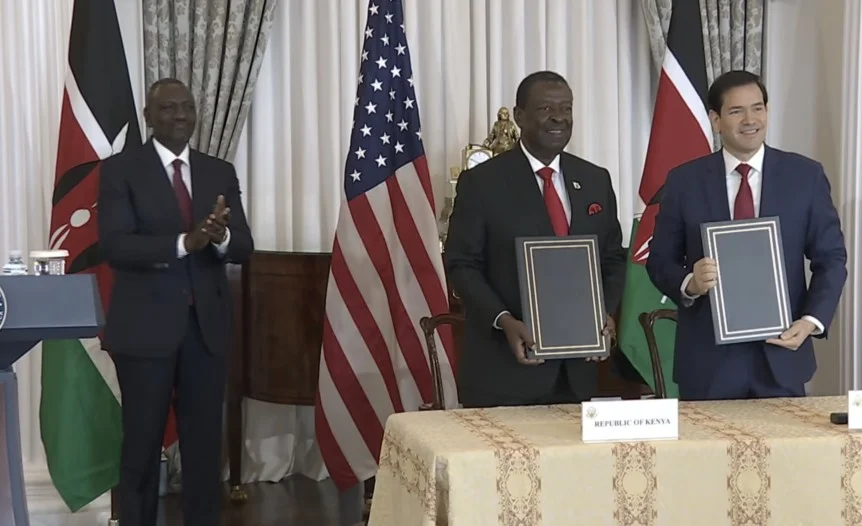
Speaking at the opening of the 67th National Council on Health in Lafia, Nasarawa State, the coordinating minister of Health and Social Welfare said development assistance for health had declined sharply in 2025. President Bola Ahmed Tinubu approved additional resources to protect gains in HIV, tuberculosis, malaria and polio immunisation.
The minister was blunt about the arithmetic. “If the US exits and we don’t increase our domestic financing, we’ll be left with a very large gap,” he said. “Sovereignty is only possible if we put our money where our mouth is.”
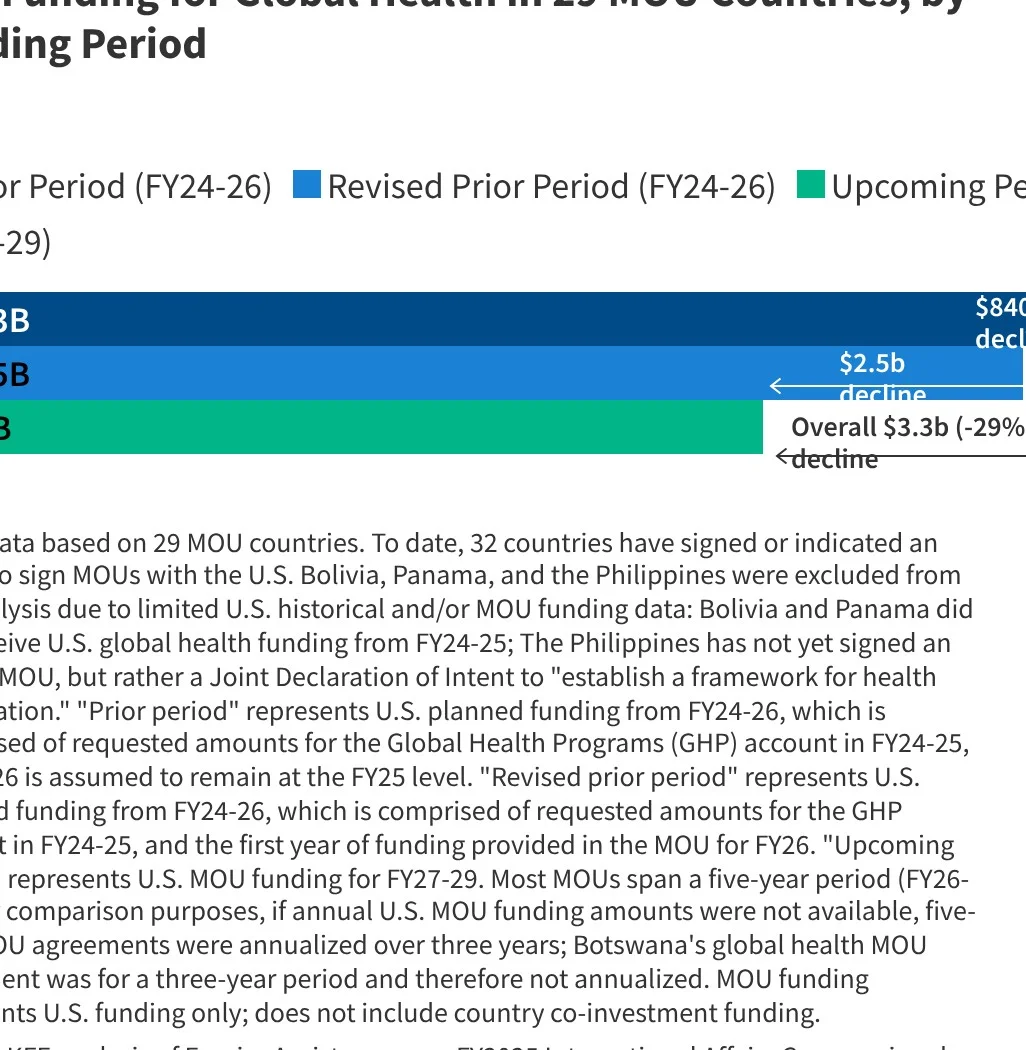
Independent analyses put the size of that gap in perspective. A KFF review of US and Global Fund reductions across the 29 countries that signed bilateral agreements estimates combined cuts of $4.3 billion between 2026 and 2029, a 24 percent drop, with 77 percent of it driven by the United States. Nigeria’s projected reduction, $280 million, is the third largest in dollar terms after Uganda and Mozambique.
A separate analysis by Public Citizen and Partners in Health, reported by Health Policy Watch, found the US plans to cut health funding to 18 countries by 59 percent of pre-2025 levels by 2030, roughly $2 billion. Rwanda faces a 97 percent reduction. Liberia, 84 percent. Burundi, 78 percent. Madagascar, 77 percent. Sierra Leone, 71 percent.
The continental picture is starker still. A Guardian report on the Accra Reset initiative notes that external financing for health in Africa contracted by close to 70 percent between 2021 and 2025. The dissolution of USAID pushed Nigeria to absorb 28,000 health workers previously employed by the agency, at a cost of $200 million.

What The Evidence Actually Establishes
Here is where the domestic financing argument splits into strong and weak claims.
The budget trend is documented. State health budgets rose from N1.97 trillion in 2023 to more than N3.3 trillion in 2026. That is a real number, on the record, announced at the sector’s highest policymaking body under the National Health Act 2014.
The service outputs are documented too. Skilled deliveries in facilities supported by the Basic Health Care Provision Fund rose from 4.8 million in 2023 to almost eight million by mid-2026. Fourth antenatal visits climbed from six million to 8.7 million. The share of BHCPF-supported facilities in hard-to-reach communities with at least two midwives or community health workers jumped from 12 percent to almost 91 percent. Health insurance enrolment moved from 16 million to nearly 24 million Nigerians in three years.
Those are administrative counts. They are not impact evaluations. Nothing in the government’s reporting isolates domestic spending as the cause of any health outcome, and no controlled comparison is offered. The proposition that more domestic money produces better health is plausible and consistent with these figures. It is not yet proven by them.
The minister’s own caveat exposes the soft spot. Allocations are not releases. A state can budget its share of N3.3 trillion and disburse a fraction of it. The health funding crisis, in other words, is a disbursement problem as much as an allocation one, and the government’s own timeline runs into 2027, an election and transition year when budget discipline historically weakens.
How To Read The Remedy Safely
The bilateral agreements come with conditions that Nigeria’s public discussion has barely touched. Countries must co-finance activities the US identifies as priorities, such as outbreak detection, epidemiologists and data capture. Those may not match what a health ministry would fund first, such as nurses and midwives.
The penalties are explicit. If Ethiopia, Kenya, Mozambique, Cameroon and Malawi miss co-financing targets, the US reduces funding by $1 for every $1 shortfall. Uganda and Cote d’Ivoire face a 2:1 reduction. The co-investments must be funds raised directly and may not include other donors or multilateral money. Malawi would have to mobilise new funding equal to 56 percent of its total health expenditure to meet its commitment.
The workforce consequences are already projected. Seven African countries will have fewer health workers by 2030. The region currently has only 46 percent of the health workers it needs, with a projected shortage of 5.85 million by the end of the decade.
What the source material does not contain is Nigeria’s own co-financing obligations, penalty terms or priority areas. The minister said the memorandum was discussed with the Nigeria Governors’ Forum and is publicly available. Until those terms are examined line by line, any claim that the gap can be closed on schedule remains a projection rather than a finding.
Risks And Alternatives Worth Weighing
The equity gap is the clearest risk. The latest household survey shows skilled health workers attending fewer than four in 10 rural births, against seven in 10 in urban areas. An increase in aggregate spending that does not move that number is not a fix.
The Emir of Shonga, HRH Dr Haliru Ndanusa Yahaya, made the sharper structural point at the same council. The problem, he argued, is not a lack of commitment but poor coordination, and the Federal Government has no territory of its own on which to implement healthcare programmes. A single national compact involving all governors, one plan and one budget, has made reform smoother. He also warned that as partners withdraw, Nigeria will have to stretch its own resources further.
Alternatives already in motion include local production. Ten factories and production lines have been commissioned, six of them this year, backed by more than N24 billion in tax waivers under a June 2024 executive order. The Accra Reset makes the strategic case: Africa produces less than 1 percent of its vaccines while carrying about 25 percent of the global disease burden, which turns regional manufacturing into a financing strategy in its own right.
Areas the ministry itself admits are behind schedule, including sodium reduction, cosmetic safety, contraceptive prevalence, laboratory management and quality improvement, are cheaper to fix than to defer.
Is Domestic Financing Worth Trying?
Yes, with conditions attached. Domestic financing is the right direction and the only durable one, but the evidence behind it is strong on direction and thin on proof. The health funding crisis will not be closed by goodwill, or by resolutions passed at councils, or by an increase in nominal budgets that never leaves the treasury.
What would settle the question is boring and measurable: quarterly release of appropriated funds, published terms of the agreements that set the deadlines, and honest reporting on whether rural births are attended by skilled hands. The remedy is worth trying. It is not yet worth claiming as a cure.
Frequently Asked Questions
How much US health funding is Nigeria set to lose?
A KFF analysis of the bilateral agreements estimates Nigeria’s reduction at $280 million, the third largest in dollar terms among the 29 countries studied, after Uganda at $370 million and Mozambique at $356 million. The cuts are phased between 2026 and 2029.
Is domestic financing proven to improve health outcomes?
Not yet proven. Nigerian state health budgets rose from N1.97 trillion in 2023 to more than N3.3 trillion in 2026, and service counts such as skilled deliveries and antenatal visits improved over the same period. But those are administrative figures, not impact evaluations, and they do not isolate domestic spending as the cause. The direction of the evidence is reasonable; the causal proof is missing.
What is the biggest practical risk in the transition away from US aid?
Release of funds, not allocation. The health minister noted that allocated money must actually be disbursed, and the transition timeline runs into 2027, an election and transition year. A second risk is equity: skilled health workers attend fewer than four in 10 rural births in Nigeria, against seven in 10 urban births.
Receive alerts for health funding crisis and more like it.
FIRST TIME REACTIONS: (health funding crisis)
Be the first to leave us a comment – Nigeria’s Health Funding Crisis: A Remedy Nobody Has Tested, down the comment section.
JOIN US ON OUR SOCIAL MEDIA:
About Paul Nwogo
Paul Nwogo is an engineer, published author, and the Head Manager at AfriLatest. He has written numerous books available on Amazon covering a diverse range of topics, including health, personal finance, relationships, work ethics, and scam survival. With his technical background and passion for writing, Paul now oversees the editorial direction of AfriLatest, delivering practical, accurate, and engaging content on trending news, music, and global lifestyle topics.
View all articles by Paul NwogoHealth and Fitness
Moisturizing Intimate Gel Mucogyne Test: No Verified Data
The moisturizing intimate gel Mucogyne reader test of 10 people has no published protocol, lab data or regulator filing, unlike agency-run product tests.

The claim that 10 readers tested a moisturizing intimate gel marketed as Mucogyne is circulating as consumer news. On the available record, it is unconfirmed. No test protocol has been published, no instrumental moisture readings have been disclosed, no named dermatologist or gynaecologist is attached to the panel, and no regulator has confirmed a product filing.
That distinction is not pedantry. The difference between a reader panel and a consumer-agency test is the difference between an anecdote and a health claim. Intimate-care products are used on mucosal tissue, where ingredient disclosure, labelling accuracy and adverse-event reporting carry more weight than scent, texture or packaging.
One point should be stated plainly for readers: the source material supplied for this article contains no primary documentation of the Mucogyne trial. The available sources cover body lotions, facial moisturizers for men, women and teenagers, and e-readers. None names Mucogyne, the 10 readers, the gel’s ingredients, the length of the trial or the measures used. That gap between the claim and the evidence is the story.

Why The Moisturizing Intimate Gel Mucogyne Reader Panel Proves Little
Ten testers is not disqualifying in itself. The Guardian’s review of body lotions used five testers, 15 products and three weeks, guided by three licensed dermatologists, and it published its method, its tester age range, its survey categories and the fact that samples were supplied by the companies, as detailed in the Guardian’s testing notes.
A panel becomes evidence only when a reader can see who tested, for how long, on which body site, against what baseline, and what counted as success. A moisturizing claim requires at least a before-and-after measure of skin hydration and of moisture loss. A satisfaction score measures preference, not moisture.
What A Verified Moisture Test Looks Like
A published benchmark exists. The Korea Consumer Agency surveyed 1,500 consumers to select eight frequently bought creams, purchased them with its own funds, and measured moisture with instruments in a room with strictly controlled temperature and humidity, as reported by SBS News.

The results contradicted price. Cetaphil Moisturizing Cream cost 66 won per millilitre and topped user satisfaction among 50 men and women in their 20s to 50s, while La Roche-Posay Cicaplast Baume B5+, at 456 won, was 6.9 times more expensive and scored lowest. Only two of the eight products, Aestura and Innisfree, won top grades for both replenishing moisture and reducing moisture loss, measured on 22 women at three and six hours. All eight passed safety screening for seven heavy metals and six preservatives, including parabens, and label volume checks.
The agency also flagged a limitation that bears directly on any intimate-gel claim: its readings came from the inner forearm, not the face. Whether a Mucogyne panel tested mucosal tissue or forearm skin has not been disclosed.
Other outlets show similar rigour at different scales. Women’s Health tested 37 moisturizers over a year with four board-certified dermatologists, checking seasonal and travel performance, per its methodology. Men’s Health routed its list through a dermatologist panel and separated occlusives, humectants and emollients, while warning that sensitive skin should avoid alcohol, artificial fragrance, dyes and parabens such as preservatives, as set out in its buying guide.
The African Evidence Gap
No African consumer agency scorecard, national regulator statement or laboratory dataset for this product appears in the material reviewed. That is an observation about the available record, not a finding that none exists.
The structural point stands. For readers in Lagos, Nairobi, Accra or Johannesburg, the only public claim attached to this product is a 10-person panel with unpublished methods. Where imported personal-care lines reach shelves faster than laboratory capacity can audit them, a reader panel can function as marketing. It is not verification.
Three outcomes are plausible, and all are forecasts rather than reported events. First, the brand publishes a full protocol, an ingredient list, patch-test data and a named laboratory, which would allow independent assessment. Second, a national regulator or independent laboratory tests the product and publishes results, as the Korean agency did. Third, the claim fades without documentation, leaving consumers with word of mouth.

The test of credibility is concrete: a pre-registered protocol, a named testing facility, a complete ingredient declaration, a stated application site, and a reporting channel for adverse reactions. Absent those, a count of 10 readers is a marketing figure rather than a measurement.
The Big Picture
Consumer journalism has learned to distrust price as a proxy for quality. The Korean data showed the cheapest cream outperforming the most expensive by a wide margin, and the Guardian’s panel found a budget cocoa butter lotion outlasting premium alternatives on hydration, even as its pump failed. Those findings were credible because the methods were visible.
The moisturizing intimate gel Mucogyne arrives without that scaffolding. Until a protocol, a laboratory and a regulator-visible ingredient list are produced, readers should treat the 10-person panel as an unverified claim about a product applied to sensitive tissue, not as tested fact. The standard already exists in other markets. Applying it here is the minimum a health-adjacent category should meet.
Frequently Asked Questions
Has the Mucogyne reader test been independently verified?
No. The source material reviewed for this article contains no protocol, instrumental moisture data, named clinical oversight or regulator filing for the 10-reader test. The claim is therefore unconfirmed.
How do consumer agencies test moisturizers differently?
The Korea Consumer Agency bought products with its own funds, surveyed 1,500 consumers to select eight creams, measured moisture instrumentally in a temperature- and humidity-controlled room, tested for heavy metals and preservatives, and published its results, including the limitation that readings came from the inner forearm rather than the face.
What should consumers look for before trusting an intimate-care moisture claim?
A published test protocol, a named laboratory, a complete ingredient declaration, the body site tested, the duration of use and a channel for reporting adverse reactions. Without these, a small reader panel reflects preference rather than measured hydration.
Receive alerts for moisturizing intimate gel mucogyne and more like it.
FIRST TIME REACTIONS:
Be the first to leave us a comment – Moisturizing Intimate Gel Mucogyne Test: No Verified Data, down the comment section.
JOIN US ON OUR SOCIAL MEDIA:
About Paul Nwogo
Paul Nwogo is an engineer, published author, and the Head Manager at AfriLatest. He has written numerous books available on Amazon covering a diverse range of topics, including health, personal finance, relationships, work ethics, and scam survival. With his technical background and passion for writing, Paul now oversees the editorial direction of AfriLatest, delivering practical, accurate, and engaging content on trending news, music, and global lifestyle topics.
View all articles by Paul Nwogo-

 Car Reviews2 weeks ago
1955 Chevy Bel Air Restomod: What SEMA Really Proves
-
Savings & Investing4 weeks ago
Hidden Medicare Fees Draining Your Retirement Savings
-
JAMB & WAEC4 weeks ago
JAMB Admission Process: What Changed And What Is Still Talk
-
World News4 weeks ago
Sheinbaum No Proof Maduro: Mexico’s Test of US Evidence
-
Movies & TV4 weeks ago
Wizkid Starboy Desire Ft Banky W Shaydee: Fact Or Fan Fiction?
-
Trend politics4 weeks ago
How 24-Hour Online Scrutiny Is Running Out Leaders











